



By Sarah Mitchell, BKin, DC, Certified Lactation Counselor | Creator of The Helping Babies Sleep Method
You finally felt like you had things figured out. Your toddler was going down well, sleeping through, and you were starting to feel like yourself again. And then — out of nowhere — it fell apart. Bedtime turned into a negotiation. Night wakings came back. Naps shortened. And you're standing in the hallway at 5:15 AM wondering what you missed.
You didn't miss anything. You're in the 15-month sleep regression — and if you're a working parent who cannot afford to absorb weeks of broken sleep, this post is written for you.
The 15-month sleep regression is real, it's common, and it has specific, identifiable causes. Once you understand those causes, you're not just coping — you're actually solving the right problem. That's the whole premise behind The Helping Babies Sleep Method: sleep regressions are not random events to wait out. They are meaningful signals from a developing child, and how you respond in the short term shapes sleep patterns that can last for months.
Let's get into it.
What Is a Sleep Regression — and Is 15 Months Really One?
Any time you hear the words "sleep regression," think growth and distraction. Your child's brain or body is developing — neurologically, physically, or psychosocially — and that development is distracting them from the business of relaxing down into sleep. Sleep regressions are not your child becoming a worse sleeper. They are your child becoming a more capable, more aware, more complex human being.
At 15 months, the regression is driven by a convergence of three distinct factors: first molar teething, the motor leap associated with mastering walking, and the beginning of genuine boundary testing as part of normal psychosocial development. Any one of these on its own can disrupt sleep. All three arriving simultaneously — which is entirely possible — can feel catastrophic to an already exhausted family.
The good news is that this is time-limited and understandable. The better news is that there are things you can do right now that will make a meaningful difference — and things you absolutely should avoid that will make it significantly worse.
What Are the Signs of the 15-Month Sleep Regression?
Knowing you're in a regression rather than dealing with a longer-term sleep habit breakdown is important, because the approach is meaningfully different. The signs to look for are:
Bedtime resistance that is new — your toddler is taking significantly longer to fall asleep, wants you to stay in the room, and is more emotionally activated at sleep time than they were a month ago. Increased night waking after a period of consolidated sleep. Naps that have shortened significantly, particularly if your toddler was previously sleeping for one to one and a half hours and is now capping at 30 or 40 minutes. Early morning wake-ups in the 5 to 5:30 AM window when your toddler was previously making it comfortably to 6 AM or later.
If several of these are happening simultaneously and they represent a change from your toddler's recent baseline, a regression is almost certainly what you're dealing with.
The Three Root Causes of the 15-Month Sleep Regression
First Molars: The Teething Nobody Warns You About
Most parents are prepared for the early tooth eruptions — the bottom and top front teeth in the first year. The first molars are a different experience entirely. These are larger, flatter teeth erupting through a wider section of gum tissue, and the discomfort they produce is meaningfully more intense than what most families experienced with the incisors.
The American Dental Association's average tooth eruption chart places the first molars between approximately 13 and 19 months, which means the 15-month window sits squarely in the middle of when this pain tends to peak.
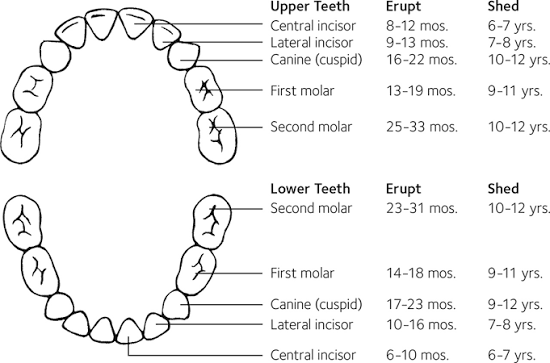
Here's the part that makes teething so confusing to diagnose: the pain occurs before the tooth has cut through the gum. Once you can actually see the tooth, the discomfort has largely passed. This means teething is almost always a hindsight diagnosis — you're living through several weeks of disrupted sleep, and only in retrospect do you realize the timing lined up with a new tooth. For any single tooth, the active pain period can span one to two weeks, with the discomfort ebbing and flowing — a genuinely terrible night followed by a completely fine day, followed by another hard night. Multiple teeth erupting simultaneously can stretch that window to four weeks or more of on-and-off disrupted sleep.
The most common sleep manifestation of first molar teething is the 5 AM waking. Your toddler surfaces naturally from a light sleep cycle in the early morning and, in that partially awake state, becomes aware of the discomfort in their gums. They cannot relax back into the next sleep cycle, and the day begins far earlier than anyone wanted.
Some signs that teething may be the primary driver include wanting to breastfeed more frequently, one finger consistently in the mouth at bedtime, ear tugging or face rubbing, and generally being more clingy and unsettled without an obvious reason. Not every child presents the same way — some seem completely unbothered during the day and fall apart at night — and that's completely normal. Teething pain is genuinely harder to manage in light sleep than during the stimulation of daytime activity.
What can you do? Offer age-appropriate pain relief before naps and at bedtime during the peak teething window. If your toddler is waking at 3 or 4 AM and the discomfort seems to be the trigger, a middle-of-the-night dose can help bridge the gap back to a more reasonable morning wake time. Cold teething objects, extra comfort during the wind-down, and slightly longer bedtime routines during this period are all reasonable accommodations.
Everything I wrote above has been my experience as a mother of two and having helped over 1000 families in the last 13 years.
However, we should also discuss a recent study worth knowing about — and reading critically.
A 2025 study published in The Journal of Pediatrics — authored by Michal Kahn, Maristella Lucchini, Emily Oster, and colleagues, using data collected via Nanit smart crib cameras — found no statistically significant differences in objective sleep metrics between teething nights and non-teething nights across 849 infants aged 3 to 18 months. Total sleep time, number of nighttime awakenings, and parental crib visits were all essentially unchanged on teething nights compared to baseline. Notably, more than half of parents in the study reported that their child's sleep was disrupted by teething — but the objective data did not corroborate those subjective reports.
This study has been cited widely as evidence that teething doesn't actually disrupt sleep, and Emily Oster summarized the finding clearly: "These results show that teething is not at fault for poor sleep."
It's a well-constructed study with a large sample and the advantage of objective measurement rather than parent recall alone. It deserves to be taken seriously. And yet, for a 15-month-old in the thick of the first molar eruption, the practical clinical picture often tells a different story — and that gap is worth understanding, because the study has several methodological limitations that matter significantly when you are applying its conclusions to your specific child.
Where the study has real limitations:
The first and most fundamental issue is how the teething window was defined. The study defined the teething period as three days centered around the day parents reported the tooth eruption — in other words, one day before the eruption, the day of, and one day after. This is a critically narrow window. Clinical literature on teething has consistently described the symptomatic period as spanning approximately four days before eruption and three days following — an 8-day window — with the pre-eruption phase frequently being the most painful, because the tooth is pressing through gum tissue that has not yet broken open. By measuring only a 3-day window anchored on the eruption day itself, the study may have missed the period of greatest discomfort entirely. If your toddler's worst nights were the four days before you could see the tooth, they would not have been captured in the teething window at all.
The second limitation is sample bias. The study participants were all Nanit users — families who have already purchased a premium smart baby monitor, are likely higher-income than average, are more likely to have already done sleep training, and may be more likely to have well-established independent sleepers whose sleep is more resilient to disruption in general. This population is not representative of all families, and findings in a sample of already-good sleepers may not translate to families whose babies are more vulnerable to sleep disruption.
Third, the study looked at infants aged 3 to 18 months with a mean age of just 8.4 months — meaning the sample was weighted heavily toward younger infants cutting earlier, smaller teeth. First molars, the teeth your 15-month-old is working on, are categorically different from incisors in terms of the surface area of gum tissue involved and the intensity of discomfort associated with eruption. A study that averages results across all teeth in a sample skewed toward younger ages and smaller teeth may significantly underestimate the sleep disruption associated specifically with first molars.
Finally, 56.5% of parents in the study administered acetaminophen or ibuprofen to manage teething symptoms. The study's own authors acknowledge this as a limitation: if parents are effectively managing pain with analgesics, the objective sleep data will not capture what sleep would have looked like without intervention. The pain is being treated — so the sleep data looks unaffected — but that does not mean the pain wasn't there.
What this means practically for your 15-month-old.
The honest read of this research is that teething — particularly for younger babies cutting incisors — may disrupt sleep less dramatically than parental perception suggests, and that parents can be prone to attributing all manner of sleep disruption to teething when other factors are at play. That is a genuinely useful corrective for a field where teething is often used as a catch-all explanation that prevents families from looking at sleep associations, schedule issues, and feeding patterns that could actually be addressed.
But for a 15-month-old cutting first molars — larger teeth, more intense eruption, a child old enough to be more aware of their own discomfort — dismissing teething as a non-factor based on this study alone would be an overcorrection. The study's narrow teething window, the limitations of video-based sleep measurement, the heavily medicated sample, and the age and tooth-type skew of the data all deserve to be weighed before concluding that the pain your child is clearly experiencing is not affecting their sleep.
Offer age-appropriate pain relief proactively at bedtime and at the 3 to 4 AM window during the active teething phase. Keep the rest of your routine as consistent as possible. And recognize that while teething is real and temporarily disruptive, it is also time-limited — and if sleep does not recover once the molar has erupted, the cause is almost certainly something else worth looking at.
The Motor Leap: Mastering Walking and What It Does to Sleep
The Motor Leap: Walking Consolidation and What It Does to Sleep
Most children take their first independent steps somewhere between 12 and 13 months on average, but walking onset and walking mastery are not the same thing. Research by Adolph and colleagues (2003) established that improvements in walking skill continue for three to four months after initial walk onset — which means that at 15 months, the majority of toddlers are still in active consolidation of a skill they have technically "started." This is a massive neurological achievement — the brain is integrating balance, coordination, proprioception, and spatial awareness in ways that have never been required before — and the evidence suggests the energy that goes into that integration does not switch off at bedtime.
A 2022 study by DeMasi, Horger, Scher, and Berger, published in Infant Behavior and Development, is the most direct research available on exactly this question. Measuring 78 infants aged 10 to 18 months using actigraphy, the authors found that "infants in the midst of walking skill acquisition had worse sleep than an age-group estimate" and that "ongoing motor skill consolidation changes the characteristics of movement during sleep and may alter sleep state-dependent memory consolidation." Critically, infants with more walking experience showed a steeper hourly increase in physical activity across the night — meaning the later hours of sleep, from around 3 to 5 AM, are disproportionately affected as the brain's motor consolidation activity accelerates. The authors propose that "changes in gross motor activity during night sleep reflect movement-dependent consolidation" — in other words, the brain is doing real, active work with the walking skill during sleep, and that work has a measurable cost to sleep continuity. This is also supported by DeMasi's broader dissertation work, which found that infants perform potentially skill-relevant movements during sleep at the onset of new motor milestones — the closest scientific language we have to the clinical observation that toddlers appear to be "practicing" at night.
This pattern typically manifests in a specific way that is quite different from teething-related waking. A parent checks on their toddler at 2 or 3 AM and finds them lying in the crib, eyes open, calm and seemingly content — not distressed, not calling out, just awake. They are not upset. The DeMasi data gives us a framework for understanding why: the brain is actively processing motor learning, and that processing is generating enough physical and neurological activity to surface the child out of sleep — particularly in the later, lighter hours of the night when sleep pressure is already low and the consolidation activity is, per the actigraphy data, at its peak.
A helpful way to think about this is in terms of your own experience with sleep. Think about the last time you were learning something new — a new sport, a new skill — or the night before something genuinely exciting. I have recently picked up Pickleball and found myself waking up in the night and thinking about it! Your brain didn't get the memo that it was time to switch off. It kept turning the thing over, rehearsing it, anticipating it. For your toddler at 15 months, walking is that thing. It is the most exciting, consuming project their nervous system has ever taken on — and at 3 AM, when the house is quiet and there is nothing else to compete for their attention, that project is still very much running.
The honest approach to motor leap waking is to keep everything else as consistent and predictable as possible while giving it time to pass. The neurological integration does settle — and once walking is fully consolidated and the brain no longer needs to rehearse the skill at night, sleep consolidates again. If sleep does not recover after the walking skill appears fully stable, it is worth looking at other factors rather than continuing to attribute the disruption to the motor milestone.
Testing Boundaries: When Your Toddler Starts Asking "Why Not?"
This is the cause that catches the most parents off guard, because nothing has changed externally — no new teeth, no new skill — and yet your previously independent sleeper has decided, with great conviction, that they would like you to sit beside them at bedtime. Every night. Indefinitely.
Erik Erikson, one of the most influential developmental psychologists of the twentieth century, identified what he called the Autonomy vs. Shame and Doubt stage as a defining period of toddler development. Erikson's framework — which has been a foundation of developmental psychology for decades — placed the onset of this stage around 18 months, but in clinical practice with toddlers, that shift often begins presenting at 15 months, particularly in children with more determined or socially aware temperaments.
🔗Erikson’s Stages of Psychosocial Development→
Stage 1 — Trust vs. Mistrust
Infancy: Birth to approximately 18 months
The central question is whether the world is a safe and reliable place. Consistent, responsive caregiving builds a foundation of basic trust. Inconsistent or neglectful care produces mistrust. This is the stage most directly relevant to infant sleep literature, as secure attachment and predictability are the core variables.
Stage 2 — Autonomy vs. Shame and Doubt
Toddlerhood: Approximately 18 months to 3 years
The child begins to assert independence — choosing, refusing, testing limits. Successful navigation builds a sense of personal autonomy. Over-control or harsh criticism produces shame and self-doubt. This is where toddler sleep resistance often sits developmentally.
Stage 3 — Initiative vs. Guilt
Preschool: Approximately 3 to 5 years
The child begins to initiate activities, ask questions, and exercise imagination. When given room to explore, initiative is the outcome. When curiosity is consistently shut down, guilt develops around the act of wanting or trying.
Autonomy vs. Shame and Doubt
At its core, this stage is about a child discovering that they have opinions and that the world can be influenced by them. They are not being manipulative — they are being developmentally appropriate. They are asking: What happens if I ask for something? What happens if I protest? What does the world do when I push back? Sleep is one of the clearest testing grounds for this, because bedtime involves separation, and separation is one of the most emotionally loaded experiences a 15-month-old encounters.
The child who was happily self-settling three weeks ago and now wants a parent to sit beside the crib isn't broken or regressing. They are doing exactly what a neurologically healthy toddler at this stage does. The question is how you respond — and that is where the outcome is determined.
How Long Does the 15-Month Sleep Regression Last?
How intensely your child experiences this regression and how long it lasts depends on three things: the underlying cause, your child's individual temperament and how you respond.
Some toddlers move through sleep regressions with relatively little drama. A week or two of slightly disrupted sleep, and then back to baseline. Other children — particularly those who feel things intensely, who are highly social, or who are especially determined — will push harder and hold out longer. This is not a parenting failure. It is temperament, and temperament is not something you created or can eliminate. It is something you work with.
The teething-driven disruptions typically resolve once the molar has erupted and the pain has passed — usually two to four weeks, though multiple teeth can extend that window. Motor leap disruptions tend to resolve within two to four weeks as the skill consolidates. Boundary-testing disruptions are somewhat more open-ended, because they are responsive to how consistently and calmly you hold your expectations. The grey area in your response is what keeps the testing going.
If sleep disruptions extend significantly beyond four to six weeks, or if what started as a regression seems to have become a new persistent pattern, it's worth looking at whether a sleep habit has been inadvertently built during the regression window — and whether that habit now needs to be gently, intentionally addressed.
What Can You Do to Help Your Toddler Through the 15-Month Sleep Regression?
The most important mindset shift to carry into a regression is this: your toddler being distracted does not mean they are incapable. The skills that were present three weeks ago are still there. They haven't been lost — they've been temporarily overshadowed by something that is genuinely compelling to your child's developing brain. Your job is to hold the container steady while the distraction passes.
Keep your routines and timing exactly as they are. A consistent bedtime routine is one of the most powerful neurological tools you have at this age. When the same sequence of events happens in the same order at the same time each evening, your toddler's brain begins to prepare for sleep before the crib even appears. Disrupting the routine during a regression — moving bedtime significantly later, skipping the nap, adding soothing steps you haven't used before — rarely helps and often extends the disruption.
Address the root cause where you can. Is this teething? Offer pain relief proactively at bedtime and at the 3 AM window when pain tends to peak. Is this a motor leap? Make sure your toddler is getting plenty of floor time and active play during the day so the neurological motor work has somewhere to go before sleep. Is this boundary testing? See the specific guidance below.
Your response: offer more comfort in the short term — but not more than you're prepared to sustain. This is the key distinction. It is completely reasonable to rock a teething toddler back to sleep at 3 AM, to sit beside the crib for a few nights of motor leap waking, or to offer an extra cuddle before bed. What matters is that you are choosing these responses intentionally, with clarity about what you're doing and why — not sliding into them out of exhaustion in a way that creates a new expectation you're not willing to maintain indefinitely. It’s also valuable to communicate with your toddler about how you’re responding. For example, “I’m going to sit here for 10 minutes while you doze back into sleep.”
Responding to Boundary Testing at 15 Months
If testing boundaries is the primary driver of your toddler's bedtime resistance, the approach that works best is acknowledgment plus a small win plus a clear, calm boundary.
The exchange might sound something like this: "I know you'd like Mummy to sit here while you fall asleep. I'm going to do the dishes — but I'll come back and check on you in five minutes." And then you follow through. You leave, you come back in five minutes, you offer a brief reassuring check-in, and you leave again with the same message.
The alternative — sitting until they fall asleep each night — is also a valid choice, but it must be made with eyes open. If you sit until they sleep tonight, you could be expected to sit until they sleep tomorrow night, and the night after that. There is no judgment in that choice, but it is worth making it consciously rather than sliding into it without realizing what you're signing up for.
What does not work — and what actually prolongs the testing — is an inconsistent response. When some nights you sit and some nights you don't, when sometimes protests bring you back and sometimes they don't, your toddler is getting unpredictable feedback and continues testing to figure out the pattern. Consistency is not harshness. Consistency is the clearest and kindest signal you can send a developing brain that is trying to understand how the world works. Be calm, compassionate, communicative, and consistent — and this too shall pass.
Erik Erikson's framework reminds us that children who navigate this stage successfully come out on the other side with a greater sense of autonomy and self-confidence. The parent's role is not to crush the testing, but to meet it with warmth and predictability, so the child learns: I have opinions. My opinions are heard. And there are still some things that stay the same.
What NOT to Do During the 15-Month Sleep Regression
Don't move your toddler from the crib to a bed. This is one of the most common mistakes families make during this regression, and it almost always makes things significantly harder. Most children are not developmentally ready for a big kid bed until around 2.5 years of age. Making the transition now, in the middle of a regression, will require you to lie beside your toddler to get them to fall asleep — and that creates a new, much harder-to-shift sleep association in a child who is now fully mobile and entirely capable of getting out of bed and coming to find you. The crib is your friend right now.
Don't close the door and disengage entirely. A 15-month-old who is testing boundaries is also, in part, asking a real question: Are you there? Do you still come when I need you? A complete non-response to that question is not the answer. The goal is not to eliminate your presence — it is to regulate how you show up. Brief, consistent, calm check-ins that offer reassurance without rocking, feeding, or extended engagement give your toddler the answer they're looking for without turning that answer into a new habit.
Don't assume this is a long-term sleep problem without giving it time. Regressions typically run their course within two to four weeks. If you dramatically overhaul your approach in week one, you may introduce changes that are harder to undo than the original regression.
When the Regression Reveals a Deeper Sleep Foundation Issue
Sometimes what looks like a regression is actually a regression sitting on top of a fragile sleep foundation — and once the temporary disruption passes, sleep doesn't fully recover because the underlying habits were never that solid to begin with.
If you're in the 15-month window and your toddler has never fully self-settled, has relied on feeding to sleep (breast or bottle), or needs rocking or patting to transfer between every sleep cycle — the regression is not the core problem. The regression is just the moment that made the core problem unsustainable.
In that case, addressing the regression alone won't be enough. The Helping Babies Sleep Method takes a five-pillar approach to sleep that looks at the full twenty-four-hour picture — your toddler's schedule and wake windows, their feeding patterns, their routines, and how you respond to night waking — because sleep at this age is almost never just a bedtime problem. It's a whole-day problem.
If feeding is still part of the sleep initiation pathway for your toddler — if a bottle of milk or nursing at bedtime is the thing that makes sleep possible — that connection will continue to drive night waking long after any developmental regression has passed. Why Sleep Training Fails When Feeding Isn't Addressed and The Feeding and Sleep Connection both go deep on why this matters and what to do about it — and they're worth reading if your nights are not recovering the way you'd expect a regression to resolve.
For toddlers who are still taking a significant bottle of milk at bedtime and waking multiple times overnight, the Snacking Cycle is also worth understanding. Toddlers who are filling up on milk at night are genuinely less hungry during the day — which keeps the nighttime feeding pattern locked in place and makes parents feel too uncertain about hunger to change anything. That cycle is very breakable, but it requires looking at the full feeding picture, not just the sleep side.
A Note for Working Parents Specifically
If you're heading back to work after the holiday weekend, or sitting in a work meeting at 9 AM running on three hours of broken sleep because your 15-month-old was up at 5:15 AM for the fourth morning running — this regression hits differently when you don't have the luxury of catching up during the day.
The most important thing to hold onto is that regressions are time-limited. You are not looking at months of this. You are looking at weeks. Hold your routines, address the root cause where you can, keep your expectations of your toddler realistic, and try not to make significant sleep changes out of desperation at 2 AM — those reactive decisions have a way of creating new problems that outlast the original regression.
If you're wondering whether working with a sleep consultant might help you navigate this faster and with more confidence, the post on How to Choose a Sleep Consultant is an honest guide to what actually matters in that decision — including why feeding background and clinical experience count for far more than a certificate on a website.
Ready for Support?
- Not sure where to start? Take the free Sleep Quiz →
- Baby 4–24 months? Explore baby sleep coaching →
- Ready to talk? Book your intro call →
- Prefer to learn on your own time? Try the Baby Online Class →
The Helping Babies Sleep Method: The Art and Science of Teaching Your Baby to Sleep by Sarah Mitchell — on Amazon or Audible— walks through the complete five-pillar framework with the context and nuance that blog posts only begin to cover.
Frequently Asked Questions: The 15-Month Sleep Regression
Is the 15-month sleep regression real, or is something else going on?
It's very real — and it tends to be more intense than many parents expect, because it's driven by not one but potentially three simultaneous developmental events: first molar teething, the motor consolidation of independent walking, and the onset of psychosocial boundary testing. The challenge is that all three can look similar at bedtime (resistance, protest, waking) while requiring slightly different responses. Identifying which one is driving the disruption is the most useful first step.
My toddler's sleep was never fully independent. Is this regression making it worse?
Almost certainly yes. Regressions amplify whatever underlying sleep habits are already present. A toddler who has always relied on nursing, rocking, or a bottle to fall asleep will lean into those associations harder during a regression. If sleep doesn't fully recover once the regression passes, the sleep habits — not the regression — are the issue that needs to be addressed. The Helping Babies Sleep Method is the right starting point for understanding what a more solid foundation looks like.
Should I try sleep training during the 15-month regression?
Generally, it's worth distinguishing between what's temporary and what's structural. If your toddler was sleeping well and this is new, give the regression two to four weeks before escalating your response. If sleep was already fragile before the regression hit, waiting for the regression to pass and then addressing the underlying sleep habits is usually the most effective sequencing.
How is the 15-month regression different from the 18-month regression?
The 15-month regression is primarily driven by physical development (molars, walking) and the very early emergence of Erikson's Autonomy vs. Shame and Doubt stage. The 18-month regression is more heavily weighted toward language development, separation anxiety, and a more consolidated version of that same boundary-testing developmental stage. Both can look similar at bedtime — resistance, protest, waking — but the 18-month version tends to be more vocally and emotionally intense because language has developed enough to add a whole new dimension to the negotiation.
My toddler wakes up at 5 AM every day. Is this a regression or just an early waker?
The 5 AM wake is one of the most consistent presentations of this regression, driven by teething pain surfacing in light sleep, motor leap activation in the early morning cycles, or simply the lower sleep pressure of the pre-dawn window making it harder to connect sleep cycles. The answer to whether it's regression-related or a true early wake pattern is usually found in the timeline — if this is new and coincides with other regression signs, it's the regression. If it predates the regression and has been consistent for months, it's a separate issue worth addressing through schedule and association work.
My toddler wants me to sit in the room every night. How do I stop this without a major battle?
Acknowledgment and a small win tend to work better than a hard stop. Rather than refusing entirely, try offering a brief, time-limited version of what they're asking: "I'll sit here for five minutes and then go do the dishes." Deliver on that promise consistently — same message, same response, every night. The key is removing the grey area. When your response is predictable, the testing typically winds down within one to two weeks because your toddler has learned what to expect. If the behavior escalates or extends well beyond that window, it may have crossed from regression into a new habit requiring more structured support.
Does this regression affect naps, or just night sleep?
Both. Naps are particularly vulnerable during the 15-month regression because the same distractibility that disrupts bedtime affects the ability to settle at nap time. Most toddlers at this age are on one afternoon nap. If naps are shortening significantly — capping at 30 to 40 minutes when your toddler was previously sleeping 90 minutes or more — the regression is almost certainly the cause. Keep the nap routine consistent, keep the timing appropriate (usually around 12 to 12:30 PM for a 15-month-old), and avoid making drastic schedule changes based on a few short nap days.
It’s possible it is related to readiness to move down to 1 nap which happens around this age.
🔗 Read more on the 2 to 1 Nap Transition here→
Could this be more than a regression? When should I seek support?
If sleep disruptions persist beyond four weeks with no improvement, if multiple night wakings are continuing at a frequency that was never your toddler's baseline, or if you've tried to address the regression and things are getting harder rather than easier — it's time to look at the bigger picture. A discovery call with Helping Babies Sleep is the place to start. We'll look at the full twenty-four-hour picture — schedule, feeding, associations, routine, and response — to identify what's actually driving the disruption and what genuinely needs to change.
Summary
The 15-month sleep regression is driven by first molar teething, the neurological work of mastering walking, and the early emergence of the psychosocial boundary-testing stage that Erik Erikson identified as central to healthy toddler development. It is time-limited, it is understandable, and it is manageable with the right response.
Hold your routines. Address the root cause where you can. Offer comfort without sliding into habits you're not prepared to sustain. Be consistent in how you respond to boundary testing — the clarity of your response is the thing that shortens the duration, not the strictness of it.
If sleep doesn't recover after the regression passes, or if the regression has revealed a fragile sleep foundation that was always there, the Helping Babies Sleep Method is the most comprehensive framework available for addressing toddler sleep in a way that accounts for feeding, development, schedule, and behavior together — because sleep at 15 months is never just one thing, and it is never solved by just one thing either.
You know your child. You are not failing. And this too shall pass — faster if you understand what's driving it.
Sarah Mitchell, BKin, DC, Certified Lactation Counselor, is the creator of The Helping Babies Sleep Method and the author of the #1 bestselling book The Helping Babies Sleep Method: The Art and Science of Teaching Your Baby to Sleep. She has worked with over 1,000 families across the San Francisco Bay Area and beyond. In-home sleep consulting is available across the Peninsula, South Bay, and San Francisco. Virtual coaching is available nationwide.
Nothing in this post constitutes medical advice. Always consult your pediatrician regarding your child's health and development.

